What Does Lasik Eye Correction Actually Change In The Cornea?

A Typical Surgery Lasik Consultation Covers These Key Steps

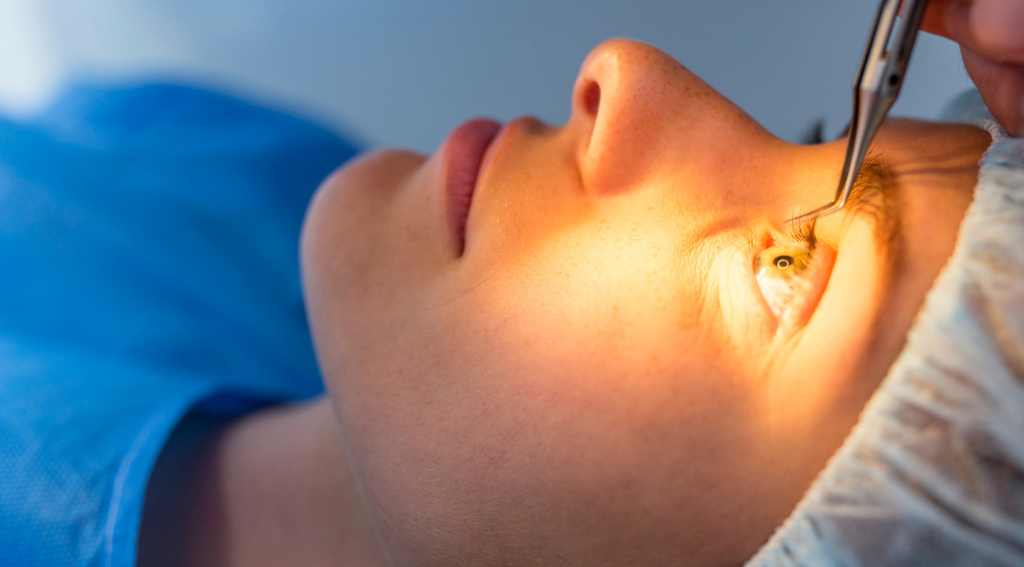
In Australia, clinics generally follow a similar pathway, even if the exact order varies. A LASIK consult typically includes pre-screening, in-depth testing, a clinical discussion, and a clear plan for next steps.

What should they do before a LASIK consult?

They usually complete a pre-appointment questionnaire and follow a few preparation rules so results are accurate. This early admin step helps the clinic spot obvious red flags, estimate suitability, and plan what tests are needed.

Many clinics ask them to stop wearing contact lenses beforehand because lenses can temporarily change corneal shape, which is an important consideration when preparing for surgery lasik. They should follow the clinic’s timeframe, which can differ between soft and rigid lenses.

What paperwork and medical history questions are covered?

They will be asked about their general health, eye health, medications, and past procedures. This matters because some conditions can affect healing, dryness, or refractive stability.

They are often asked about autoimmune conditions, diabetes, pregnancy or breastfeeding, eye injuries, chronic dry eye, and prior infections. They may also be asked about their occupation, sport, and screen time, because these influence risk and aftercare planning for a LASIK consult.

How do clinics confirm their current prescription and vision goals?

They measure how well they see now and what they want to achieve, then confirm whether expectations are realistic. This includes checking their prescription, their best-corrected vision, and whether both eyes work well together.

They may be asked what they dislike about glasses or contacts, and what matters most, such as night driving, sport, or reducing dependence on spectacles. Clear goals upfront help the surgeon tailor advice during the LASIK consult.
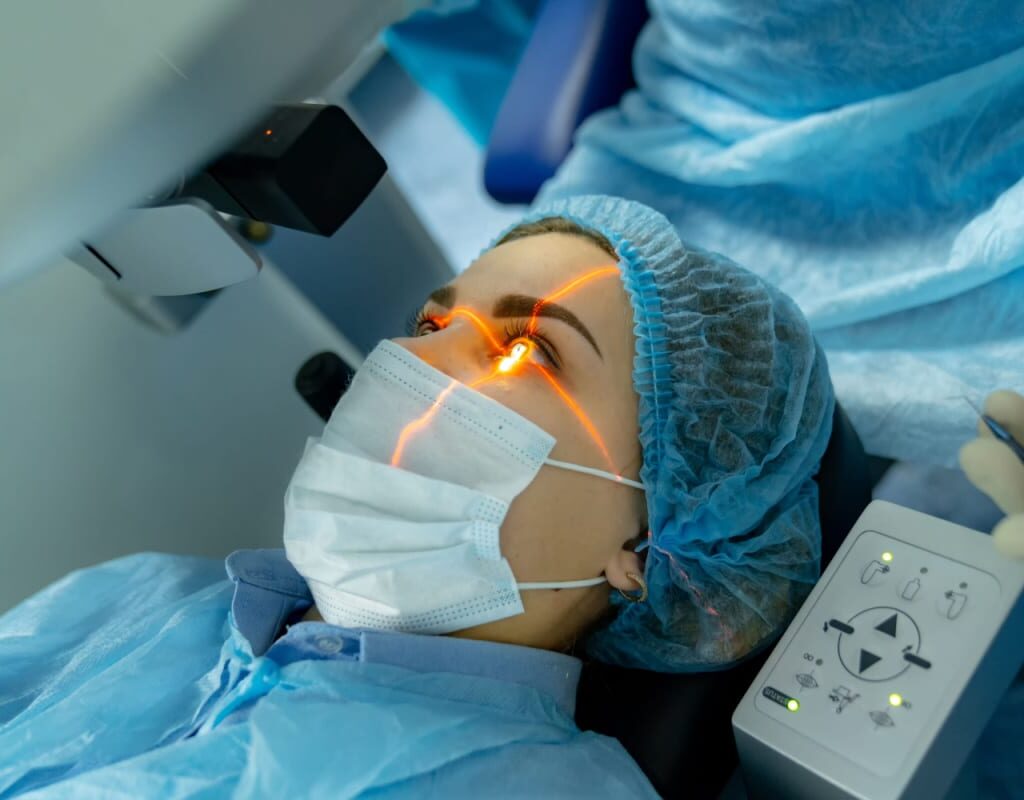
A Typical Surgery Lasik Consultation Covers These Key Steps The current image has no alternative text. The file name is: Lasik-Eye-Surgery-1-1024x640-1.jpeg Replace

What eye scans and measurements are performed?

They should expect a series of scans that map the cornea and the eye’s focusing system. These scans help confirm whether their cornea is thick and regular enough for treatment.

Common tests include corneal topography or tomography (shape and curvature), pachymetry (thickness), and pupil size in different lighting. These results help screen for conditions like keratoconus risk and guide how a LASIK consult is interpreted.

Why is corneal thickness checked so carefully?

Corneal thickness influences how much tissue can be safely reshaped. If too much is removed, the cornea can become unstable, so this is a key safety gate.

They are not just looking at a single number. The surgeon also considers corneal shape, distribution of thickness, and how much correction is required, because all of these affect whether LASIK is appropriate within the LASIK consult.

How is dry eye assessed during the appointment?

They usually check tear quality and eyelid health because dryness can worsen temporarily after laser eye surgery. If they already have dry eye, symptoms may be more noticeable during recovery.

The clinic may ask about gritty sensation, fluctuating vision, contact lens intolerance, and screen-related dryness. They might also examine meibomian glands and tear film stability, then recommend treatment before proceeding with surgery as part of the LASIK consult plan.

What happens during the refraction and vision testing?

They will go through refraction, which is the “which is better, one or two?” test, plus checks of visual acuity and focusing. This confirms the prescription and whether it is stable.

They may have both subjective refraction and automated measurements. If their prescription has changed recently, the surgeon may recommend waiting until it becomes stable, which is a common consideration during a LASIK consultation in Australia.

Will their eye pressure be measured, and why does it matter?

Yes, intraocular pressure is commonly measured because it can relate to glaucoma risk and overall eye health. It is also helpful for building a baseline before any procedure.

Eye pressure is interpreted alongside corneal thickness, because thicker or thinner corneas can affect readings. If anything looks suspicious, they may be referred for further assessment before moving forward from a LASIK consult.

Why do they dilate pupils, and what does that check?

They may use dilating drops to examine the retina and optic nerve in more detail. This helps rule out retinal tears, degeneration, or other conditions that could affect safety or visual outcomes.

After dilation, their near vision may be blurry and they may be light sensitive for a few hours. Many clinics suggest they do not drive themselves home, which is practical planning that often comes up during a LASIK consult.

What does the surgeon evaluate to confirm suitability?

The surgeon weighs the test results against their prescription, corneal structure, eye health, and lifestyle risks. The goal is to identify who is likely to benefit and who should consider other options.

Suitability decisions are often based on corneal regularity, thickness, dryness, pupil size, prescription range, and stability. If they are not a strong candidate, a good LASIK consult should clearly explain why and what alternatives exist.

What alternatives might be discussed if LASIK is not ideal?

They may be offered PRK, SMILE, or implantable contact lenses (ICL), depending on their eyes and prescription. Each option has different recovery timelines and risk profiles.

For example, PRK may suit thinner corneas but can involve longer surface healing. SMILE may be preferred for some prescriptions and corneal considerations. In Australia, many clinics cover these comparisons directly as part of a LASIK consult.

How are risks and side effects explained in plain language?

They should expect a clear discussion of common side effects and less common complications. A quality explanation helps them make an informed decision rather than relying on marketing.

Topics often include dry eye, glare and halos at night, fluctuating vision during healing, infection, inflammation, under or over-correction, and the potential need for enhancement. The surgeon should also explain how risks apply to their specific measurements from the LASIK consult.

What should they ask about night driving, glare, and halos?

They should ask how their pupil size, prescription, and corneal profile may affect night vision. Some people notice halos or starbursts after surgery, especially early on.

The clinic can explain whether wavefront-guided or topography-guided approaches are relevant, and what is typical during recovery. This is a practical, lifestyle-focused part of a LASIK consult that often influences confidence.

How do they talk about presbyopia and reading glasses?

If they are in their 40s or older, they should expect a discussion about presbyopia, which is the natural loss of near focusing. Even with perfect distance correction, they may still need reading glasses later.

They may discuss monovision, where one eye is set for near and the other for distance, or other strategies. A LASIK consult should be upfront that laser surgery does not stop natural age-related changes.

What does the consultation cover about the procedure day?

They will usually get a step-by-step overview of what happens on surgery day, including timing, drops, and what they will feel. This helps reduce anxiety and sets realistic expectations.

They are often told the laser portion is brief, but preparation and checks take longer. They will also be told they need someone to drive them home, and they may be given instructions about makeup, perfumes, and eye products before surgery, which is standard in a LASIK consult.

What aftercare and recovery steps are explained?

They should receive clear instructions on drops, hygiene, activity restrictions, and follow-up visits. These rules are designed to reduce infection risk and support stable healing.

Common guidance includes avoiding swimming, spas, and eye rubbing for a period, while taking screen breaks if dryness becomes worse. They may also receive a schedule for check-ups during the first days and weeks, with these instructions usually outlined clearly after LASIK eye correction.

How do they estimate costs and what is included in Australia?

They will usually be given a written quote that explains what the fee covers. In Australia, inclusions vary by clinic, so they should check details rather than assume.

They may ask whether the price includes scans, surgeon fees, follow-ups, enhancement policies, and aftercare drops. Transparent pricing is part of a good LASIK consult because it prevents surprises and helps them compare clinics fairly.

What red flags should they watch for during a LASIK consult?

They should be cautious if the clinic rushes testing, avoids explaining results, or pressures them to book immediately. Laser eye surgery is elective, so they should feel comfortable taking time to decide.

They should also watch for vague answers about risks, dry eye management, or suitability criteria. A trustworthy LASIK consult should show them their scans, explain what they mean, and document recommendations.

How do they decide whether to proceed after the appointment?

They proceed when they understand benefits, risks, costs, and recovery, and their test results support safety. If they feel uncertain, they can request a copy of results and seek a second opinion.

They should weigh lifestyle needs such as sport, shift work, and night driving, plus practicalities like time off work and childcare. A strong LASIK consult ends with a clear, pressure-free plan, including what to do next and when to re-check if they are not ready yet.

What is the simplest takeaway from a typical LASIK consult?

A LASIK consult is essentially a safety and suitability investigation, followed by an honest conversation about outcomes. If their eyes are suitable, they should leave with a clear plan for procedure day and recovery.

If their eyes are not suitable, they should still leave with answers and alternatives. Either way, a well-run LASIK consult in Australia should help them make a confident, informed decision based on their own measurements and goals.
A Typical Surgery Lasik Consultation Covers These Key Steps

The current image has no alternative text. The file name is: Lasik-Eye-Surgery-1-1024x640-1.jpeg
Replace

FAQs (Frequently Asked Questions)

What should I do to prepare before a LASIK consult in Australia?

Before your LASIK consult, you should complete a pre-appointment questionnaire and follow the clinic’s preparation guidelines. This often includes stopping contact lens wear for a specified period, as lenses can temporarily alter corneal shape. Following these steps ensures accurate test results and helps clinics assess your suitability effectively.

What medical history information is important during a LASIK consultation?

During the consultation, you’ll be asked about your general and eye health, medications, past eye procedures, and conditions like autoimmune diseases, diabetes, pregnancy or breastfeeding status, chronic dry eye, and prior infections. Additionally, lifestyle factors such as occupation, sports activities, and screen time are discussed to tailor risk assessment and aftercare planning.

How do clinics determine if my vision goals are realistic for LASIK surgery?

Clinics measure your current prescription and best-corrected vision while discussing what you want to achieve with surgery. They evaluate whether both eyes work well together and ask about your preferences, such as reducing dependence on glasses or improving night driving vision. This helps surgeons set clear expectations and personalize advice during the consult.

What eye tests are performed during a LASIK consult to assess suitability?

You can expect comprehensive scans including corneal topography or tomography to map corneal shape and curvature, pachymetry to measure corneal thickness, and pupil size measurements under different lighting conditions. These tests help detect conditions like keratoconus risk and determine if your cornea is suitable for safe laser reshaping.

Why is assessing corneal thickness crucial before LASIK surgery?

Corneal thickness determines how much tissue can be safely reshaped during LASIK without compromising corneal stability. Surgeons consider not only thickness but also corneal shape, thickness distribution, and the degree of correction needed. Ensuring adequate thickness is key to preventing complications post-surgery.

How are risks and side effects of LASIK explained during the consultation?

A thorough LASIK consult includes clear discussions about common side effects like dry eye or visual disturbances such as glare and halos, as well as less common complications. Clinics aim to provide plain-language explanations so you can make an informed decision beyond marketing messages.
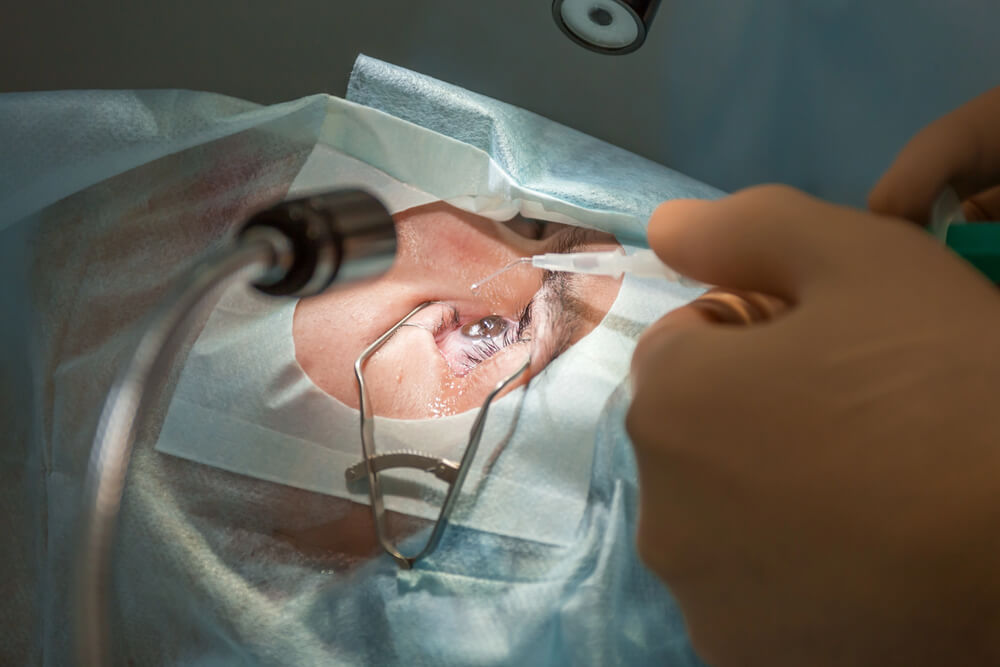
What Does Lasik Eye Correction Actually Change In The Cornea?

What Does Lasik Eye Correction Actually Change In The Cornea?

In Australia, the procedure is commonly offered in major cities like Sydney, Melbourne, Brisbane, Perth, and Adelaide, with suitability confirmed through detailed pre-op scans and measurements.

What part of the cornea does LASIK eye correction change?

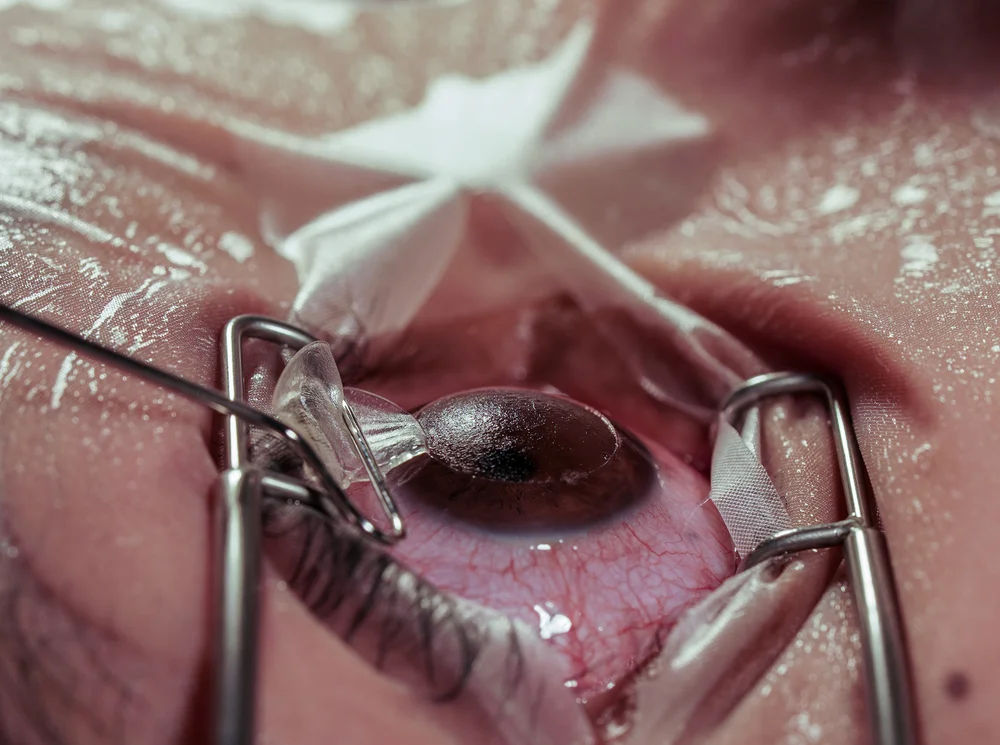
Lasik eye correction primarily changes the corneal stroma, the thick middle layer that provides most of the cornea’s shape. The laser reshapes this layer so the cornea bends light differently.

The corneal epithelium (the surface “skin”) is lifted with the flap rather than fully removed, which is a key difference from PRK-style surface treatments.

How does LASIK eye correction reshape the cornea to fix vision?

Lasik eye correction changes the cornea’s curvature so images land sharply on the retina. For myopia, it typically flattens the central cornea; for hyperopia, it steepens the central zone by removing tissue in the periphery; for astigmatism, it evens out an irregular curve.

The amount removed is tiny, usually measured in microns, but it can meaningfully alter focusing power.

What exactly is the flap in LASIK eye correction?

The flap is a thin, hinged layer made from the front of the cornea, usually including epithelium and part of the anterior stroma. Lasik eye correction uses this flap to access the underlying tissue for laser reshaping, then places the flap back down.

In Australian clinics, the flap is commonly created with a femtosecond laser, though some providers may still use a microkeratome depending on their systems and patient factors.

What does the laser remove during LASIK eye correction?

Lasik eye correction removes a calculated amount of stromal tissue in a specific pattern unique to the person’s prescription and corneal measurements. This tissue removal is what produces the new corneal shape.

The laser does not remove the whole surface layer like a surface ablation procedure. Instead, the flap provides access and then acts like a natural bandage when repositioned.

Does LASIK eye correction change the cornea’s strength?

Yes, Lasik eye correction can reduce corneal biomechanical strength because it removes tissue and involves a flap, and the cornea is a load-bearing structure. That is why screening focuses heavily on thickness, shape, and stability to reduce the risk of post-op ectasia.

Australian refractive surgeons typically use corneal topography and tomography to identify higher-risk patterns before recommending any laser procedure.

How does LASIK eye correction affect corneal nerves and dryness?

Lasik eye correction can temporarily disrupt corneal nerves, particularly those in the front layers, which can reduce tear reflex and contribute to dry eye symptoms. Many people improve over time as nerves recover, but management can be important early on.

Australian clinicians often recommend lubricating drops, lid hygiene, and dry eye assessment pre-op, especially for those with screen-heavy work or pre-existing dryness.

What Does Lasik Eye Correction Actually Change In The Cornea?

Does LASIK eye correction change the cornea’s surface quality?

LASIK eye correction can improve functional optics by smoothing the overall corneal curvature for clearer focus, although it may introduce subtle higher-order aberrations in some cases. These changes can affect night vision, glare, or halos, particularly in people with larger pupils or higher prescriptions.

Modern wavefront-guided or topography-guided approaches used in Australia aim to better match the treatment to the person’s optical system and corneal shape.

How does LASIK eye correction affect corneal thickness?

Lasik eye correction reduces corneal thickness because the laser removes stromal tissue, and the flap also has a set thickness. This is why a “residual stromal bed” must remain above a safety threshold to keep the cornea stable.

Australian pre-op workups usually include pachymetry mapping, not just a single thickness number, because thickness distribution matters.

What changes in the cornea are permanent after LASIK eye correction?

The stromal reshaping from Lasik eye correction is intended to be permanent, because the tissue that is removed does not grow back. The flap typically adheres and stabilises, but it never heals exactly like untouched cornea.

While the shape change is long-lasting, a person’s eyes can still change over time from normal ageing, hormonal factors, or lens changes inside the eye.

Can the cornea “regrow” after LASIK eye correction?

No, the removed stromal tissue does not regrow in the same way skin might. Lasik eye correction relies on a stable structural change, not temporary swelling or healing.

However, the cornea can undergo subtle wound-healing responses, and some people experience small prescription shifts over years, which is one reason enhancements are sometimes discussed.

How does LASIK eye correction differ from PRK in what it changes?

Lasik eye correction reshapes the stroma under a flap, while PRK removes the epithelium and reshapes the surface stroma directly. Both aim to change corneal curvature, but they affect healing patterns and nerve disruption differently.

In Australia, PRK may be preferred for some people with thinner corneas, certain corneal shapes, contact sport participation, or flap-related concerns, depending on surgeon guidance.

What do Australian clinics measure before LASIK eye correction to protect the cornea?

They measure corneal thickness, curvature, and elevation patterns to detect conditions like keratoconus or subtle irregularity. They also assess tear film quality, pupil size in low light, and overall eye health to reduce complication risk.

Many Australian providers use topography and tomography together, since these can reveal both front and back surface changes, which is important when deciding if Lasik eye correction is appropriate.

What risks are directly related to corneal changes from LASIK eye correction?

The main cornea-linked risks include dry eye symptoms, night vision disturbances, flap complications, infection, inflammation, and rare biomechanical instability like ectasia. The overall risk profile varies by prescription level, corneal thickness, and pre-op shape.

Australian surgeons generally focus on careful selection and conservative planning to minimise how much tissue must be removed while still meeting visual goals.

How quickly do corneal changes settle after LASIK eye correction?

Initial corneal healing happens quickly, often within days, but fine visual stability can take weeks as the tear film normalises and the cornea settles. Some people notice fluctuations early, especially in dry environments or with heavy screen use.

In Australian conditions, air conditioning, heaters, and coastal winds can all affect dryness, so aftercare often includes regular lubrication and follow-up checks.

Does LASIK eye correction change the cornea’s ability to handle impact?

Because a flap is created, some clinicians consider trauma risk in people who play contact sports or work in environments with higher eye-injury risk. Lasik eye correction does not usually limit day-to-day activities long-term, but lifestyle can influence procedure choice.

In Australia, people involved in sports like rugby, AFL, martial arts, or certain trades may be counselled about PRK or other options depending on their risk profile.

What does LASIK eye correction not change in the eye?

Lasik eye correction does not change the lens inside the eye, the retina, or the underlying causes of age-related near vision loss (presbyopia). Someone may still need reading glasses later even if distance vision is excellent after laser treatment.

It also does not prevent future eye diseases, so regular eye checks in Australia remain important, particularly for glaucoma risk, diabetes-related eye changes, or family history concerns.

When might corneal changes from LASIK eye correction be less predictable?

Higher prescriptions, very dry eyes, irregular corneal topography, or borderline thickness can make outcomes less predictable or increase risk. Healing responses vary between individuals, and some may be more prone to residual prescription or night symptoms.

Australian surgeons commonly manage this by recommending different procedures, planning a conservative correction, or advising against surgery if corneal safety margins are not strong. These decisions are often discussed during a LASIK consultation, where suitability and potential risks can be assessed before treatment.

How can they tell if LASIK eye correction changed the cornea as intended?

Follow-up checks confirm vision, corneal clarity, and shape stability using refraction tests and corneal imaging. They also assess tear film and ocular surface health, because dryness can mimic blur even when reshaping is accurate.

In Australia, most clinics schedule several reviews in the first weeks to months to ensure the corneal outcome matches the planned correction and to address symptoms early.

What is the simplest way to describe what LASIK eye correction changes?

Lasik eye correction changes the cornea’s shape by removing microscopic tissue under a thin flap, so the eye focuses light more precisely. That reshaping is the core mechanism behind clearer uncorrected vision for many people.

The decision to proceed should be guided by corneal measurements, lifestyle needs, and a clinician’s advice based on Australian standards of screening and follow-up care.

What Does Lasik Eye Correction Actually Change In The Cornea?

FAQs (Frequently Asked Questions)

What part of the cornea does LASIK eye correction primarily change?

LASIK eye correction primarily reshapes the corneal stroma, which is the thick middle layer responsible for most of the cornea’s shape. The procedure involves lifting a thin flap that includes the epithelium and part of the anterior stroma to access this layer for laser treatment.

How does LASIK reshape the cornea to correct different vision problems?

LASIK changes the cornea’s curvature to focus light accurately on the retina. For myopia (short-sightedness), it flattens the central cornea; for hyperopia (long-sightedness), it steepens the central zone by removing peripheral tissue; and for astigmatism, it smooths out irregular curves. The laser removes microscopic amounts of stromal tissue tailored to each individual’s prescription.

What is the significance of the corneal flap in LASIK surgery?

The flap is a thin, hinged layer created from the front portion of the cornea, including epithelium and some anterior stroma. It provides access to underlying tissue for precise laser reshaping and is then repositioned to act as a natural bandage, promoting faster healing compared to surface ablation procedures.

Does LASIK eye correction affect the strength and stability of the cornea?

Yes, because LASIK removes stromal tissue and involves creating a flap, it can reduce corneal biomechanical strength. Therefore, thorough pre-operative screening using corneal topography and tomography is essential in Australian clinics to assess thickness, shape, and stability and minimize risks like post-operative ectasia.

How does LASIK impact corneal nerves and dry eye symptoms?

LASIK can temporarily disrupt corneal nerves in the anterior layers, which may reduce tear production reflexes leading to dry eye symptoms. Most patients experience nerve recovery over time, but early management with lubricating drops, lid hygiene, and pre-operative dry eye assessments are commonly recommended in Australia.

What permanent changes occur in the cornea after LASIK surgery?

The stromal reshaping achieved through LASIK is intended to be permanent since removed tissue does not regenerate. While the flap adheres post-surgery, it never heals exactly like untouched corneal tissue. Despite lasting shape changes, natural aging or other ocular factors can still alter vision over time.

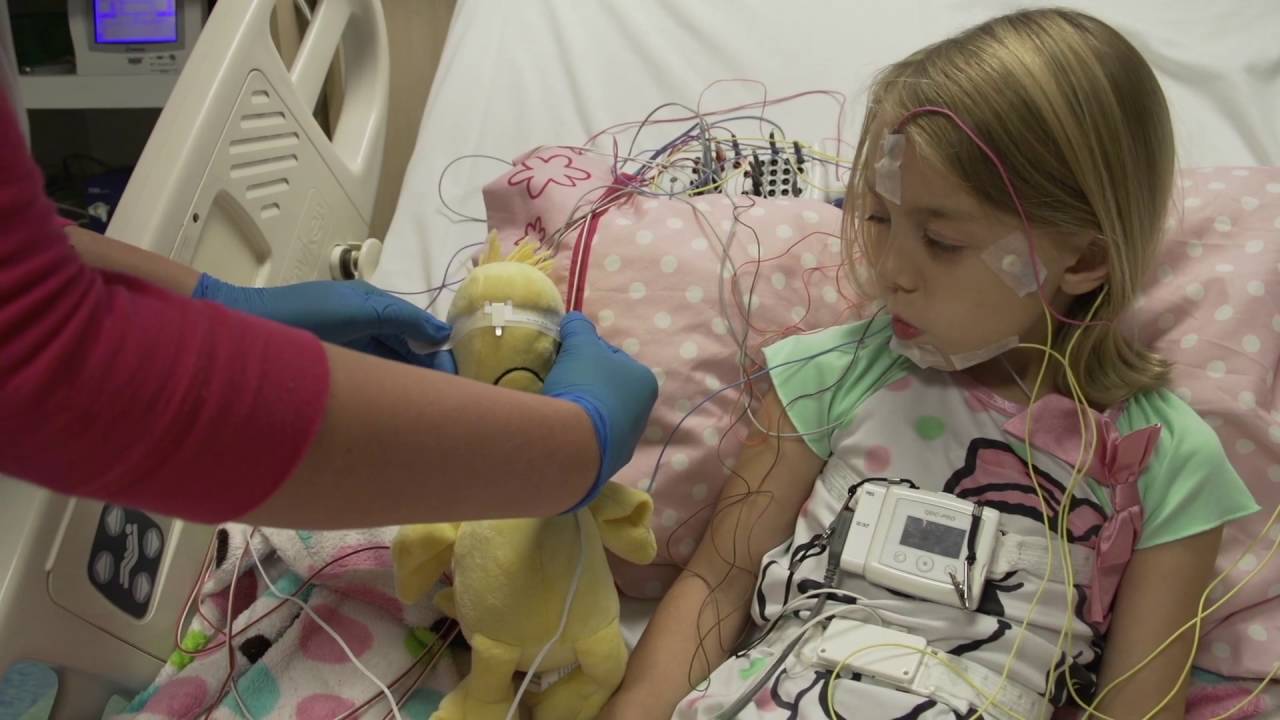
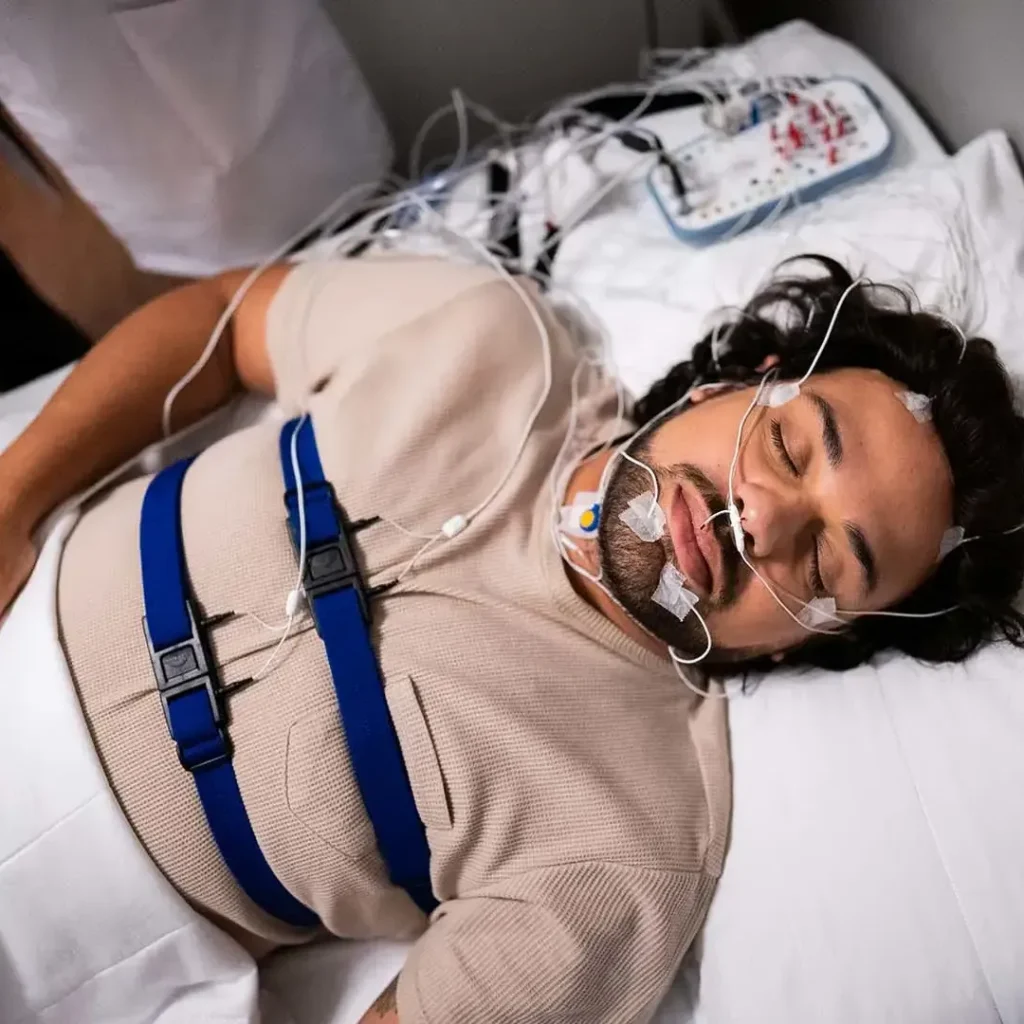
Home Sleep Study Brisbane

Is a Home Sleep Study Brisbane Better Than In-Clinic Testing?

For many people in Brisbane, a home sleep study can be a better first step than in-clinic testing because it is cheaper, faster to book, and more comfortable. But it is not automatically “better” for everyone, since some symptoms and medical histories require the extra detail a lab can capture.

The right choice depends on what they need to diagnose, how complex their sleep problem looks, and what their doctor is trying to rule out when considering a home sleep study Brisbane compared to in-clinic testing.

Is a home sleep study in Brisbane accurate enough for sleep apnoea?

Yes, for straightforward suspected obstructive sleep apnoea, home sleep studies are usually accurate enough to confirm the condition and guide treatment. They measure breathing, oxygen levels, heart rate, and airflow patterns that reveal apnoea events.

Accuracy can drop if they have other sleep disorders, significant heart or lung disease, or if the sensors are applied poorly. Most providers include instructions and phone support to reduce recording errors.

Home Sleep Study Brisbane

What does an in-clinic sleep study measure that home testing can miss?

In-clinic testing measures far more signals, including brain activity (EEG), eye movements, muscle tone, limb movements, and detailed sleep staging. That extra data helps identify issues beyond breathing, such as parasomnias, seizures during sleep, narcolepsy, and complex movement disorders. Understand more about narcolepsy.

Home studies mainly focus on breathing-related sleep disorders. If they need a full picture of sleep architecture and arousals, a lab study can be more informative.

Which option is more comfortable for most people?

A home sleep study is usually more comfortable because they can sleep in their own bed, follow their normal routine, and avoid an unfamiliar environment. That often leads to a more typical night of sleep.

In-clinic studies can feel intrusive due to multiple sensors and the clinic setting. However, some people sleep better in a controlled environment, especially if their home is noisy or chaotic.

Is a home sleep study in Brisbane faster to access?

Often, yes. Home sleep studies are commonly easier to schedule because they do not require an overnight clinic bed and staffing on the same scale. Many services can arrange equipment pickup or delivery quickly.

In-clinic studies can involve longer wait times, especially during busy periods. If their symptoms are affecting safety, such as drowsy driving, speed of access may matter.

How do costs typically compare between home and in-clinic testing?

Home sleep studies are typically cheaper because they use less equipment, fewer channels, and less overnight staffing. For people paying privately, that price difference can be significant.

In-clinic testing costs more due to the facility, sleep technicians, and comprehensive monitoring. Depending on their circumstances, rebates or referral pathways may change the final out-of-pocket cost, so they should confirm pricing before booking. Lean more about diagnosing clinical sleep disorders.

Home Sleep Study Brisbane

When is in-clinic testing the better choice?

In-clinic testing is often better when symptoms suggest something more complex than obstructive sleep apnoea or when prior home testing was inconclusive. It can also be the safer option for people with significant medical comorbidities where close monitoring is important. See everything you need to know before getting a sleep study Adelaide.

It may be recommended if they have suspected central sleep apnoea, neuromuscular conditions affecting breathing, unusual nighttime behaviours, severe insomnia needing detailed assessment, or persistent symptoms despite treatment.

Can a home sleep study be “better” for treatment setup like CPAP?

For many uncomplicated cases, yes. A home sleep study can confirm obstructive sleep apnoea and support a streamlined pathway to CPAP therapy, especially when paired with a clinician review and follow-up.

However, some people need more nuanced titration or investigation before treatment. If they have complex breathing patterns, significant oxygen drops, or mixed apnoea types, a lab-based assessment can better guide next steps.

What should they consider before choosing a provider in Brisbane?

They should look for a service that includes proper clinical oversight, clear instructions, and a formal report reviewed by a qualified sleep physician or experienced clinician. Good follow-up matters because the test is only useful if it leads to an accurate diagnosis and a practical plan.

They should also ask what happens if the recording fails, whether a repeat is included, and how quickly results are delivered to them and their referring doctor.

So, is a home sleep study Brisbane better than in-clinic testing?

A home sleep study in Brisbane is often better as a first-line option for suspected obstructive sleep apnoea because it is convenient, comfortable, and cost-effective. In-clinic testing is better when the situation is complex, the risks are higher, or they need detailed sleep staging and broader diagnostic coverage.

The simplest rule is this: if their symptoms look straightforward, home testing is usually enough; if anything feels unclear, severe, or unusual, a clinic study is more likely to provide answers.

Home Sleep Study Brisbane

FAQs (Frequently Asked Questions)

What are the advantages of a home sleep study in Brisbane compared to in-clinic testing?

A home sleep study in Brisbane is often cheaper, faster to book, and more comfortable since you can sleep in your own bed and follow your normal routine. It is a convenient first step for diagnosing straightforward obstructive sleep apnoea.

Is a home sleep study accurate enough to diagnose sleep apnoea?

Yes, for straightforward suspected obstructive sleep apnoea, home sleep studies usually provide accurate measurements of breathing, oxygen levels, heart rate, and airflow patterns to confirm the condition and guide treatment. However, accuracy may decrease if other complex conditions are present or if sensors are not applied properly.

When should I consider an in-clinic sleep study over a home test?

An in-clinic sleep study is better when symptoms suggest complex sleep disorders beyond obstructive sleep apnoea, such as parasomnias, seizures during sleep, narcolepsy, or movement disorders. It is also recommended if prior home testing was inconclusive or if you have significant medical comorbidities requiring close monitoring.

How do comfort levels compare between home and in-clinic sleep studies?

Most people find home sleep studies more comfortable because they can stay in their familiar environment and maintain their usual bedtime routine. In-clinic studies involve multiple sensors and an unfamiliar setting which some may find intrusive, though certain individuals may prefer the controlled environment of a clinic.

Are home sleep studies quicker to access than in-clinic tests in Brisbane?

Often yes. Home sleep studies typically have shorter wait times because they do not require overnight clinic beds or extensive staffing. Many providers offer quick equipment pickup or delivery services, making them accessible especially when timely diagnosis is important.

How do costs differ between home and in-clinic sleep studies?

Home sleep studies generally cost less due to simpler equipment and reduced staffing needs. In contrast, in-clinic tests are more expensive because of comprehensive monitoring and facility fees. Costs can vary based on private payment options, rebates, or referral pathways, so it’s advisable to confirm pricing before booking.

Sleep Study Adelaide

Everything You Need to Know Before Getting a Sleep Study Adelaide

A sleep study in Adelaide helps clinicians figure out why someone is not sleeping well, snoring loudly, or feeling exhausted during the day. It records key body signals overnight so a sleep physician can diagnose issues like obstructive sleep apnoea, insomnia patterns, or movement disorders.

For many people, the hardest part is not the test itself. It is knowing what to expect, what it can and cannot show, and how to prepare so the results are useful when considering a sleep study Adelaide and ensuring the process provides accurate insights into sleep health.

What is a sleep study, and what does it measure?

A sleep study records sleep and breathing to identify disruptions that someone cannot see at home. It typically tracks airflow, oxygen levels, breathing effort, heart rate, body position, and snoring.

In more comprehensive studies, it can also measure brain activity and sleep stages. That extra detail helps clinicians separate problems such as apnoea, insomnia, and unusual movements during sleep.

Who should consider a sleep study in Adelaide?

They should consider a sleep study if they have symptoms that suggest a sleep disorder that needs confirmation. Common triggers include loud snoring, choking or gasping at night, witnessed pauses in breathing, morning headaches, or persistent daytime sleepiness.

Sleep Study Adelaide

It can also be relevant for people with high blood pressure, type 2 diabetes, or weight gain where sleep apnoea is suspected. Some may be referred because of fatigue-related driving risk or work safety concerns. Kowledge about type 2 diabetes.

How do they know if they need a home study or an in-lab study?

The best option depends on symptoms, medical history, and what the clinician needs to rule in or out. Home sleep studies are often used when obstructive sleep apnoea is strongly suspected and there are no complex medical issues.

In-lab studies are more suitable if they have significant heart or lung disease, suspected central sleep apnoea, unusual movements, possible narcolepsy, or when prior testing was unclear. In-lab testing can also capture more signals and sleep stages.

What happens during a home sleep study?

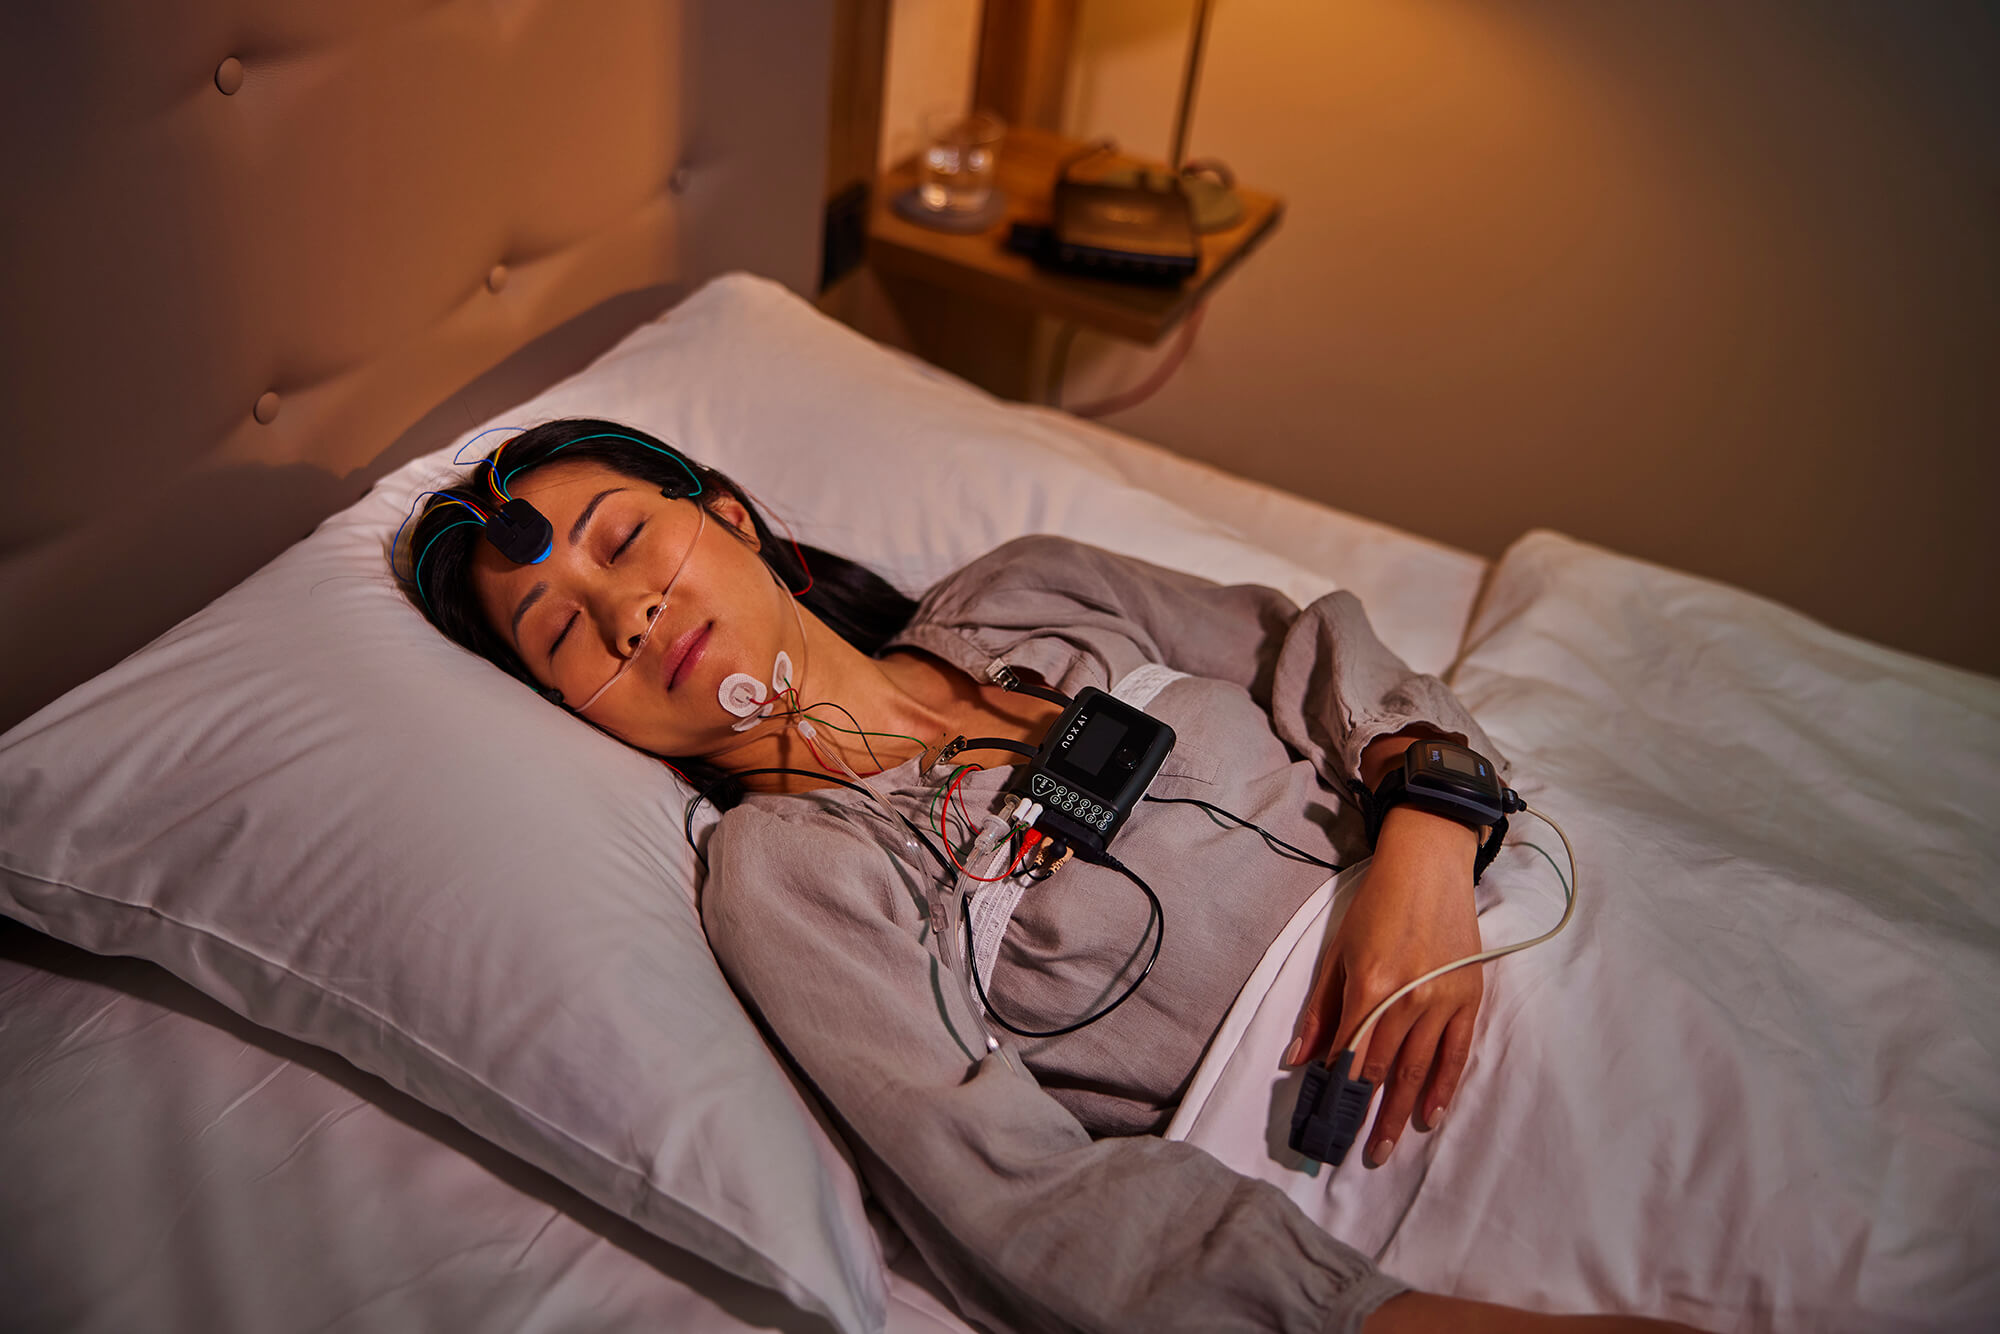
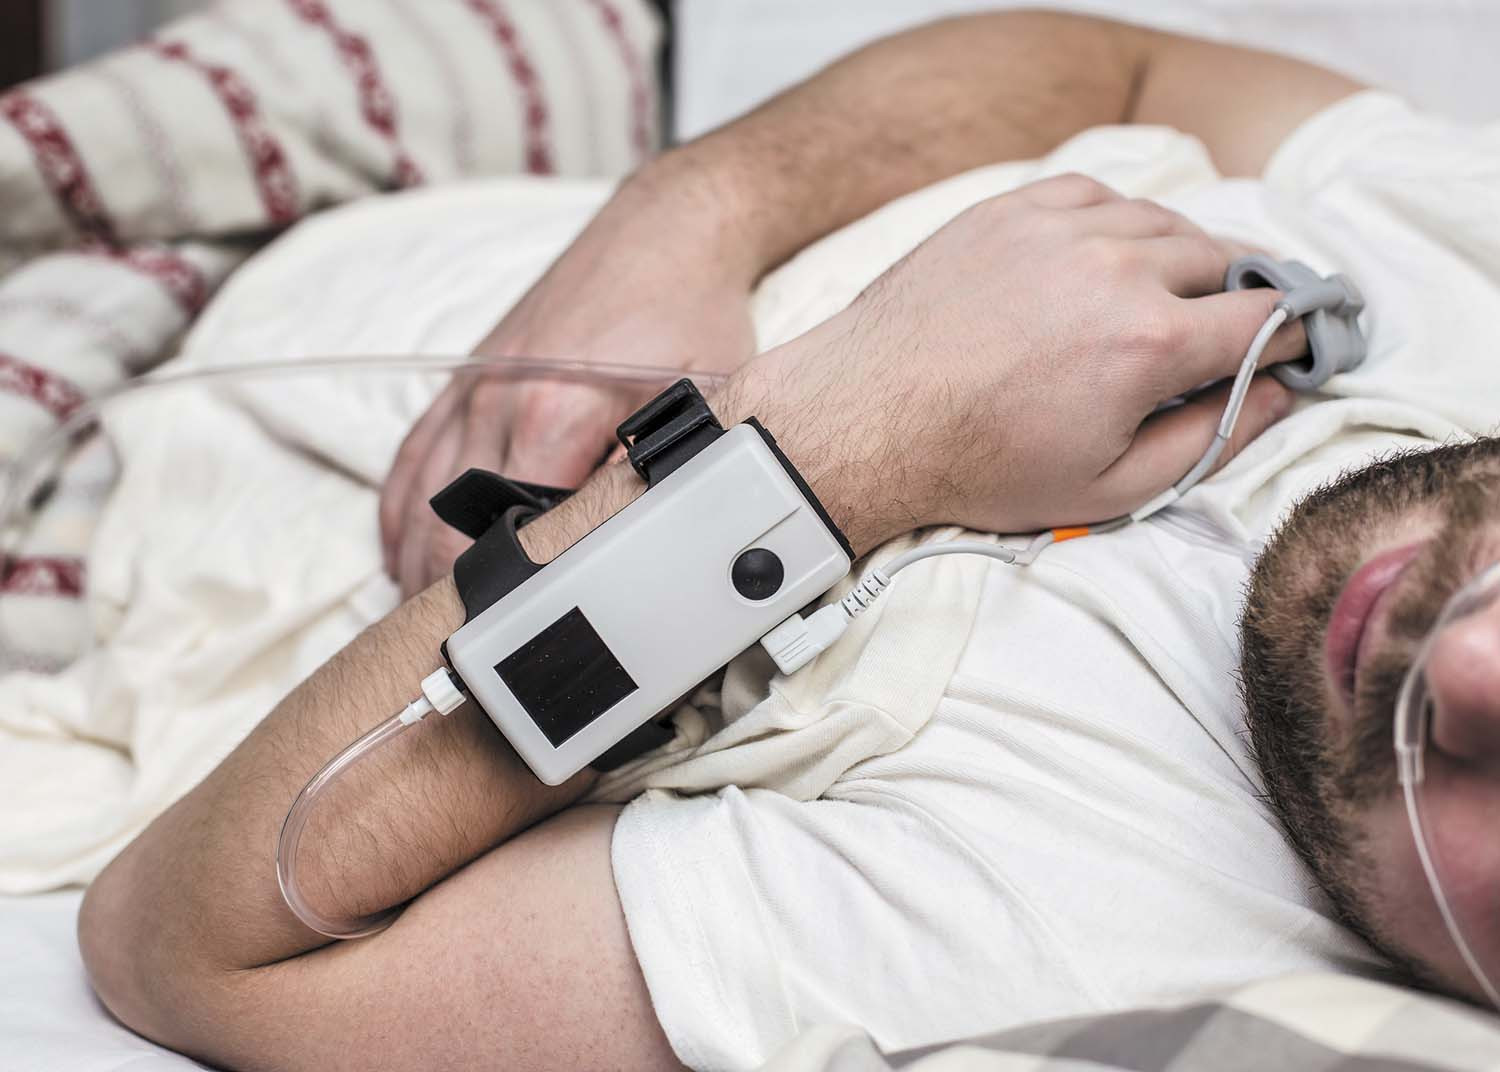
A home sleep study usually involves a small portable device they wear for one night. It commonly includes a nasal cannula to measure airflow, a finger probe for oxygen, and belts around the chest or abdomen for breathing effort.

They set it up before bed, sleep in their own environment, then return the equipment the next day. Because it is done at home, the night can feel more normal, though sensors can still take a little getting used to.

What happens during an in-lab sleep study?

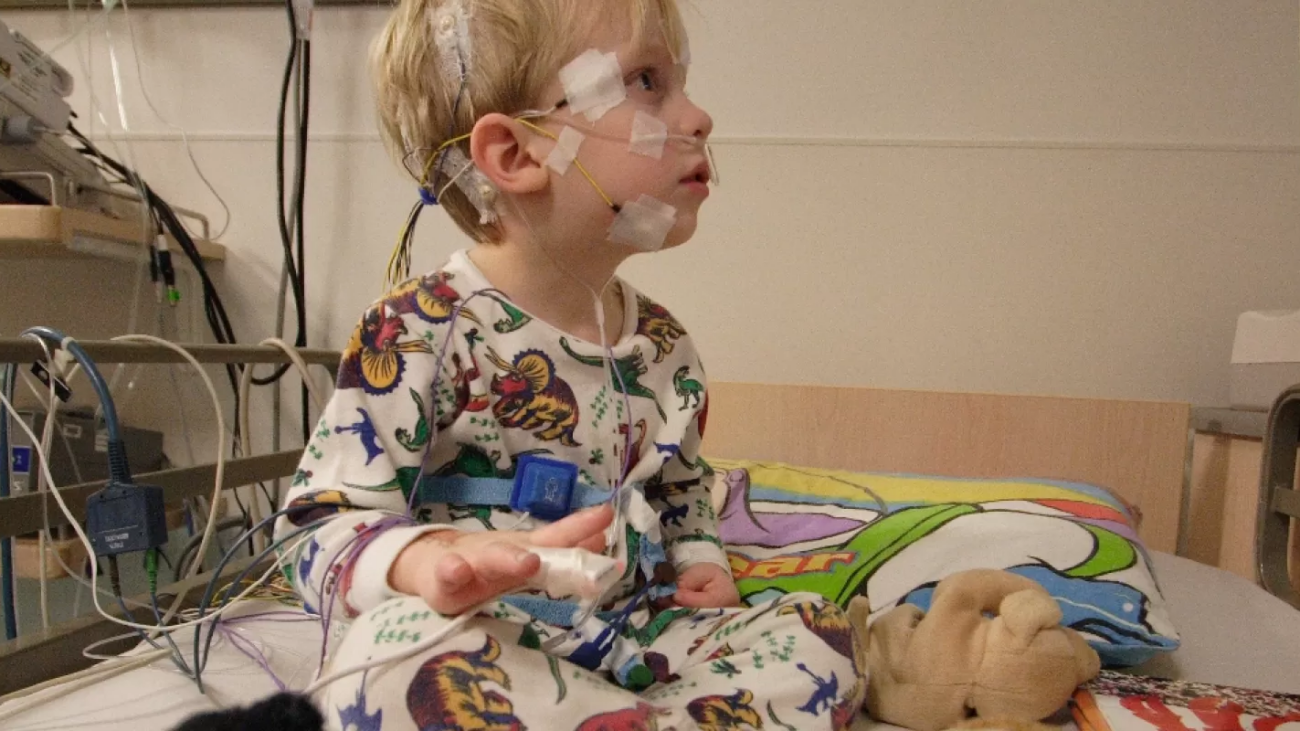
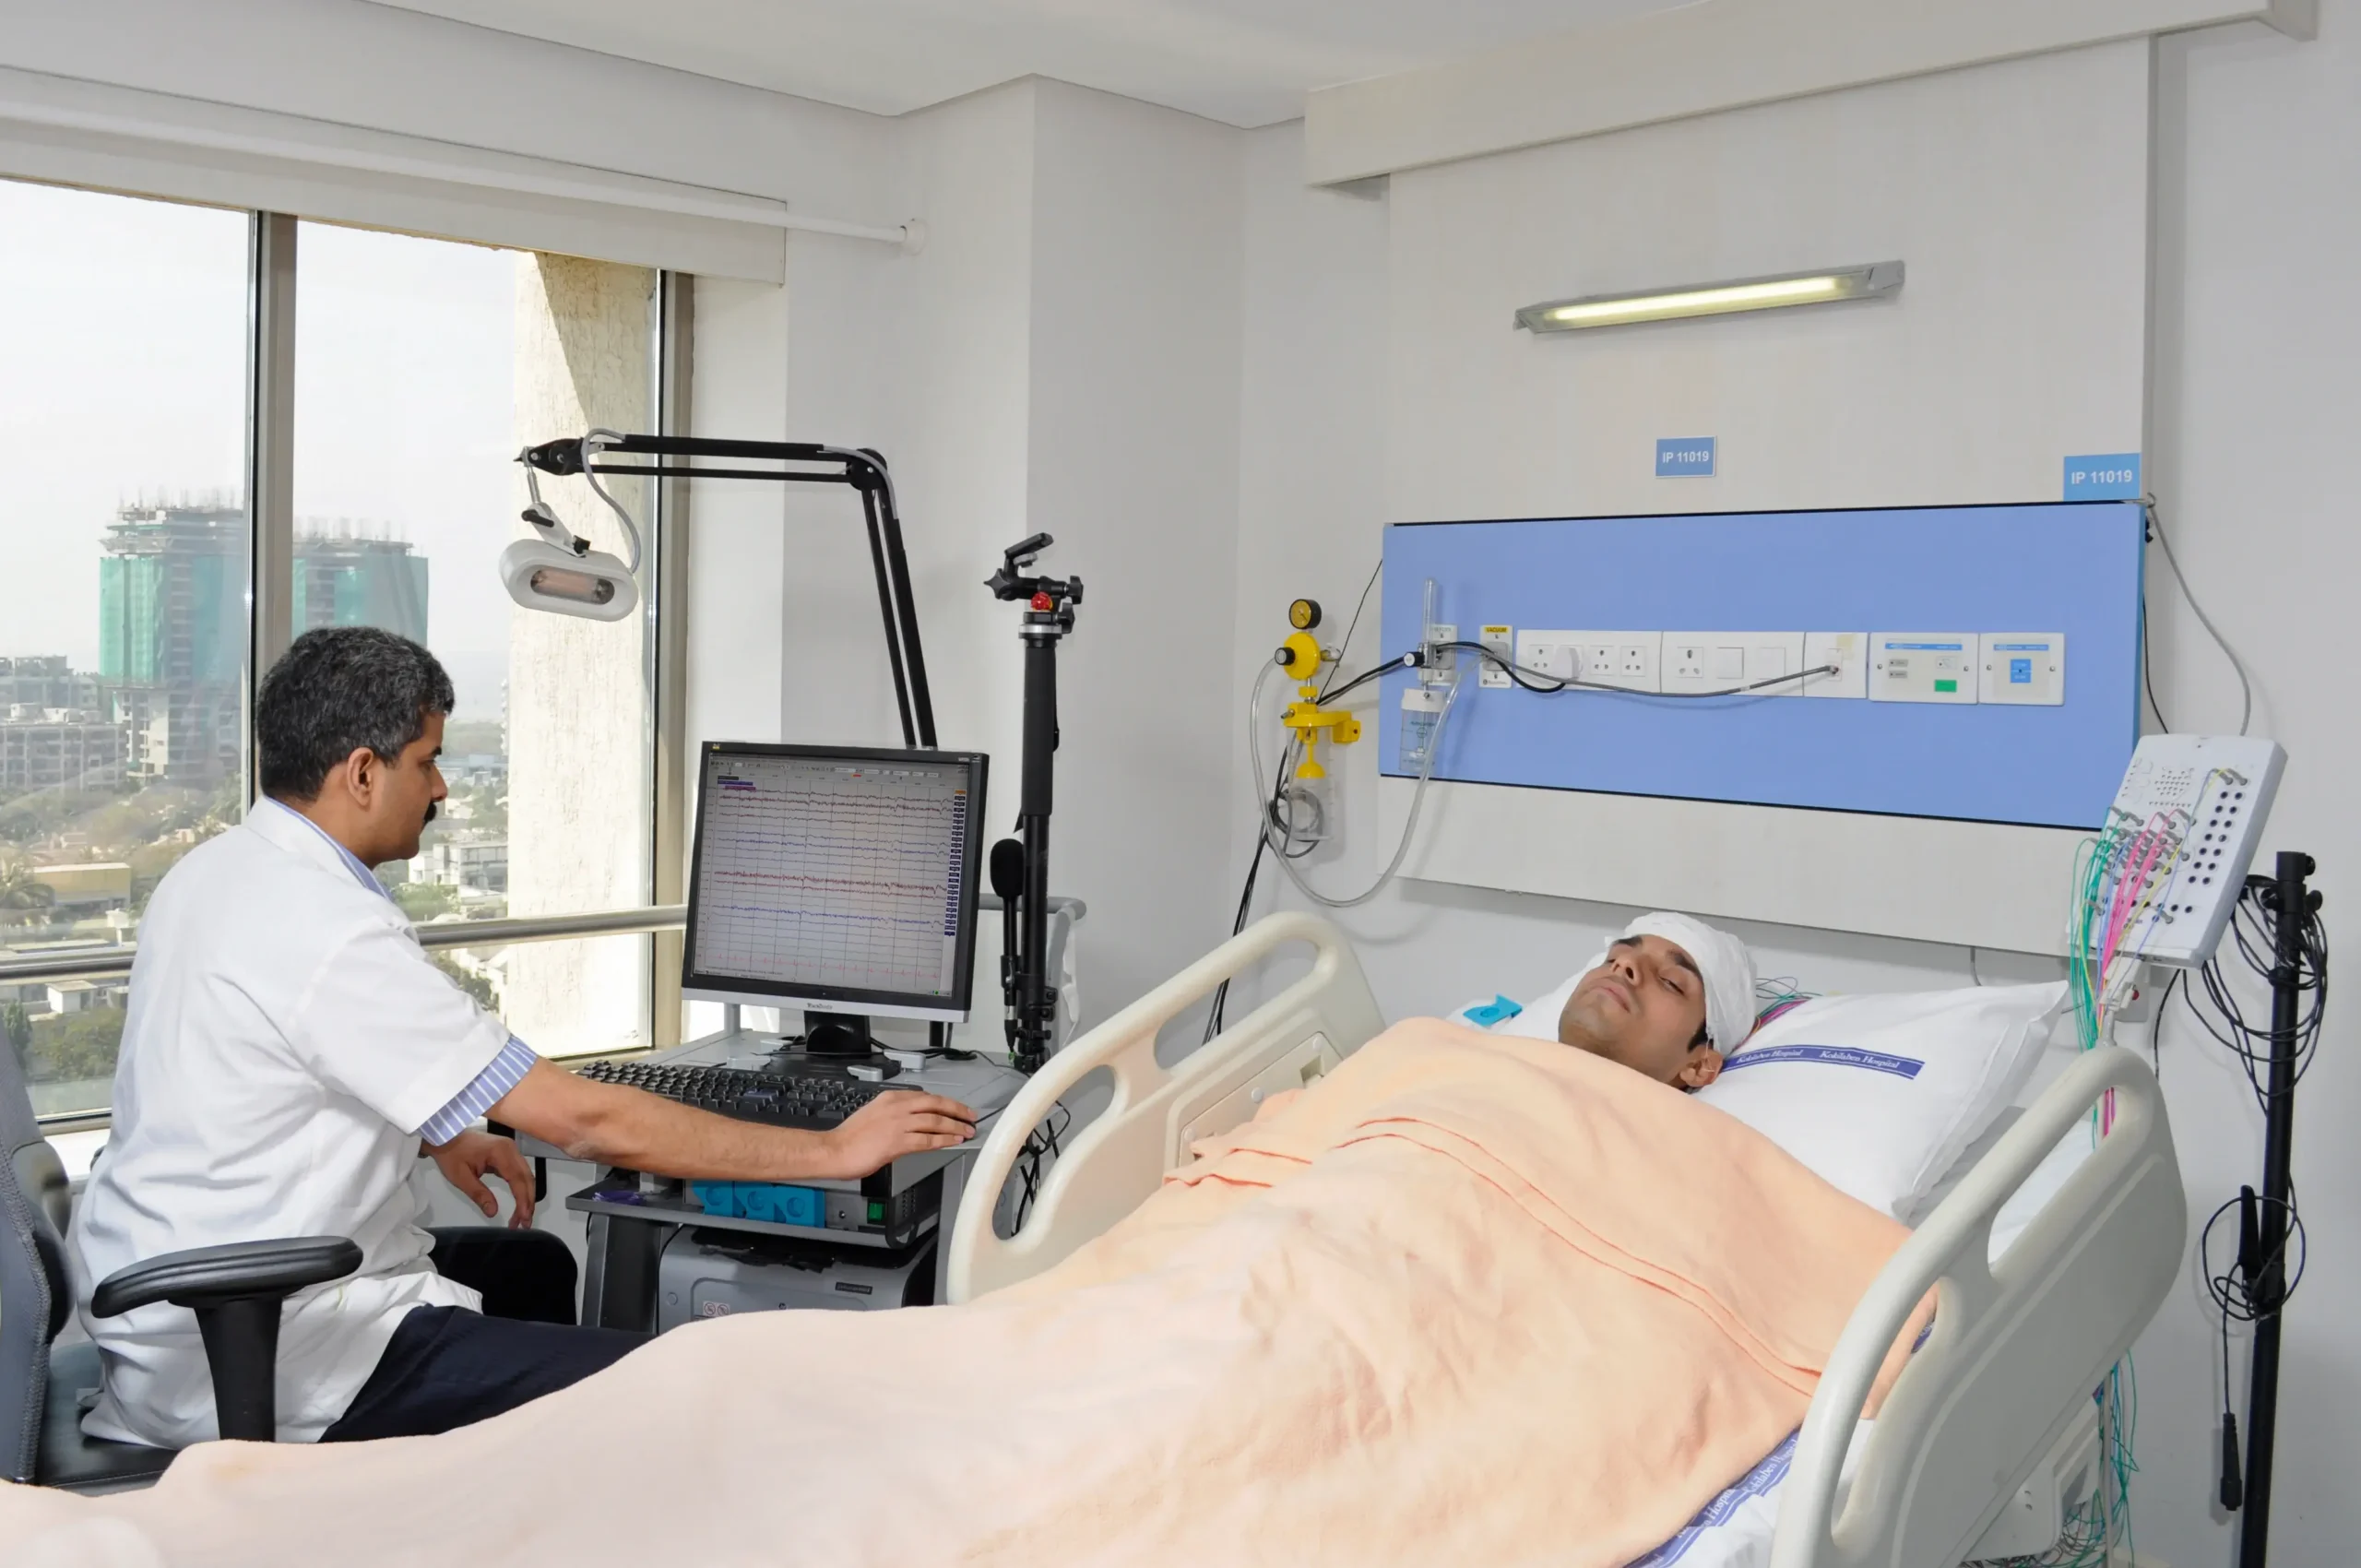
In-lab studies are done overnight in a sleep clinic where trained staff monitor signals throughout the night. They are fitted with sensors that may include scalp electrodes for sleep stages, eye movement sensors, muscle sensors, breathing measures, and oxygen monitoring. Overnight diagnostic sleep studies.

Staff can troubleshoot sensors if they fall off and may add extra monitoring if needed. The environment is designed for sleep, but it still differs from home, which can slightly affect how quickly they fall asleep.

How should they prepare the day of the sleep study?

They should aim for a typical day so the test reflects normal sleep. Most clinics recommend avoiding naps, limiting caffeine later in the day, and avoiding alcohol because it can worsen snoring and apnoea.

They should follow medication instructions from the referring clinician and bring their usual bedtime items if attending in-lab. Clean, dry skin can help sensors stick properly, so heavy lotions and hair products are best avoided.

Sleep Study Adelaide

What should they bring if the sleep study is in a clinic?

They should bring comfortable sleepwear, toiletries, and any nighttime medications they normally take. If they use a mouthguard or other sleep device, they should bring it unless told otherwise. See home sleep study Brisbane better than in-clinic testing?

Many people also bring a book or headphones to wind down. They can ask ahead about parking, check-in times, and whether they can eat a light snack before settling in.

What do sleep study results usually show?

Results usually show whether breathing is repeatedly interrupted during sleep and how severe those interruptions are. For suspected sleep apnoea, clinicians often focus on indices that count breathing events and how low oxygen levels drop.

They may also comment on snoring, sleep position effects, heart rate changes, and sleep quality. For in-lab studies, results can include sleep stage distribution and arousal patterns.

How long does it take to get results and next steps?

It often takes days to a couple of weeks, depending on the clinic and whether a sleep physician needs to review a detailed report. Once results are in, they may be offered a follow-up appointment to explain what was found.

If sleep apnoea is diagnosed, next steps can include CPAP therapy, oral appliances, weight management support, positional therapy, or referral to an ENT specialist. If apnoea is not present, the clinician may investigate insomnia, restless legs, or circadian issues.

What are the most common concerns, and what should they know?

Many worry they will not sleep, but clinicians can still get useful data even if sleep is shorter than usual. Others worry the equipment will hurt, but sensors are designed to be non-invasive and safe.

Some also assume snoring always equals apnoea, which is not always true. A sleep study is helpful because it separates simple snoring from clinically significant breathing disruption that needs treatment.

sleep study process

How can they make sure their sleep study is as accurate as possible?

They should follow setup instructions carefully and try to sleep as normally as possible. For home studies, correct placement of sensors and keeping the device on overnight are the biggest factors.

They should also tell the clinician about typical sleep habits, alcohol use, medications, and nasal congestion, since those can affect breathing. If the night was unusual, they should mention it so the report is interpreted in context.

FAQs (Frequently Asked Questions)

What is a sleep study in Adelaide and what does it measure?

A sleep study in Adelaide records key body signals overnight to help clinicians diagnose sleep issues. It measures airflow, oxygen levels, breathing effort, heart rate, body position, and snoring. More comprehensive studies also track brain activity and sleep stages to identify problems like obstructive sleep apnoea, insomnia, or movement disorders.

Who should consider undergoing a sleep study in Adelaide?

Individuals experiencing symptoms such as loud snoring, choking or gasping at night, witnessed breathing pauses, morning headaches, or persistent daytime sleepiness should consider a sleep study. It is also relevant for people with high blood pressure, type 2 diabetes, weight gain where sleep apnoea is suspected, or those with fatigue-related driving risks or work safety concerns.

How do I know if I need a home sleep study or an in-lab sleep study?

The choice depends on your symptoms and medical history. Home sleep studies are suitable when obstructive sleep apnoea is strongly suspected without complex health issues. In-lab studies are better for those with significant heart or lung disease, suspected central sleep apnoea, unusual movements during sleep, possible narcolepsy, or unclear prior tests. In-lab studies capture more detailed signals including sleep stages.

What should I expect during a home sleep study?

During a home sleep study in Adelaide, you will wear a small portable device overnight that includes sensors like a nasal cannula for airflow, a finger probe for oxygen levels, and belts around the chest or abdomen to measure breathing effort. You’ll set up the equipment before bed and return it the next day. Although done at home for comfort, some sensors may take getting used to.

How can I prepare for my sleep study to ensure accurate results?

To prepare for your sleep study in Adelaide, aim for a typical day by avoiding naps and limiting caffeine later in the day. Avoid alcohol as it can worsen snoring and apnoea. Follow medication instructions from your clinician and keep skin clean and dry to help sensors stick properly. For in-lab studies, bring comfortable sleepwear and any usual nighttime devices like mouthguards.

What happens after my sleep study and how long until I get results?

Sleep study results usually take from a few days up to two weeks depending on the clinic. A sleep physician reviews the data and you may have a follow-up appointment to discuss findings. If obstructive sleep apnoea is diagnosed, treatment options include CPAP therapy, oral appliances, weight management support, positional therapy, or referral to an ENT specialist. If no apnoea is found, other issues like insomnia or restless legs may be investigated.

Repetitive Books For Language Learning

Repetitive Books For Language Learning

In  Books, Toddlers and Language, I told you about how reading repetitive books with infants and toddlers can be a great way to entice them into using language with you. These books are great for any child and they can also be essential tools for helping children with diagnoses such as apraxia or autism. 

Here, then, is a list of my favorite repetitive books. Is one missing? E-mail us at [email protected] and share it. We’ll add it to the list. Happy Reading!

  • Brown Bear by Bill Martin Jr. and Eric Carle
  • Polar Bear by Bill Martin Jr. and Eric Carle
  • The Very Hungry Caterpillar, by Eric Carle
  • Chugga Chugga Choo Choo by Kevin Lewis
  • Tugga Tugga Tug Boat by Kevin Lewis
  • Good Night Moon by Margaret Wise Brown
  • Blue Hat, Green Hat by Sandra Boynton
  • Doggies by Sandra Boynton
  • 5 Little Monkeys Jumping On The Bed by Eileen Christelow
  • 5 Little Ducks by Raffi
  • I Went Walking by Sue Williams
  • Jump Frog Jump by Robert Kaplan
  • The Napping House by Audrey Wood
  • Time For Bed by Mem Fox
  • Dear Zoo by Rod Campbell
  • Trashy Town by Andrea Zimmerman
  • Yummy Yucky by Leslie Patricelli
  • Quiet Loud by Leslie Patricelli
  • Bear on a Bike by Stella Blackstone

Other Resources
All Kinds of Talk: Using Your Language to Change Your Child’s
Everything You Need to Know Before Getting a Sleep Study Adelaide

Grow Your Child's Language

Using Expansion and Extension To Grow Your Child’s Language

As a pediatric speech-language therapist, I often use indirect language facilitation strategies to help grow a child’s language.

I’ve written about these strategies before, such as when I wrote about how the way you talk to your child impacts his language learning and when I described how to use self-talk and parallel talk.

This time around, I”m pulling out a couple more indirect language facilitation strategies that parents can put in their language-boosting tool box: expansion and extension. These both fall under the category of “indirect language facilitation” because they are built around a child’s utterance (what the child says) and because they do not require a response from the child.  This differs from strategies that are based on the principles of applied behavioral analysis (ABA).  ABA techniques usually involve a specific, targeted response from the child that is prompted or elicited, required, and reinforced. (As a slight aside, I certainly think that both child-directed/indirect language facilitation techniques AND clinician-directed/ABA strategies can be- and often should be – used together.  And, there is a time and a place where each is more effective than the other. But that’s a different post all together).

Grow Your Child's Language

Expansion and extension are very similar. The most important part of these techniques is that the parent uses them to respond to the child.  This requires that a child initiate (start) an interaction somehow.  The child might point, or vocalize, or say a word …. anything that starts an interaction. Then a parent either expands on or extends what the child has to say.

In my experience in working with parents, the hardest part about these strategies is that they require parents to wait.  Often, when we are in teaching mode, we are inclined to instruct- to direct a child,  to tell a child what to do or how to do it.  Again, there is most definitely a place for this (heaven knows I have directed many children to do many things in my career).  There also need to be times, however, when we respond to a child’s language instead of directing it. And that’s where expansion and extension come in.

So how are they different? When we EXPAND a child’s utterance, we keep the child’s word order the same and expand it just slightly to make it a bit longer and/or more grammatically correct.   When we EXTEND a child’s utterance, we simply respond to the child’s utterance in a conversational way, providing a bit of new information that is related to what the child had to say.

So, if a child says, “Puppy outside….”

We can expand this utterance by saying, “Puppy IS outside”.  We’ve expanded because we’ve kept his word order the same (puppy is the first word, outside is the second- and we haven’t changed this), but we’ve made it just a bit longer (in this case we made it just one word longer) and more grammatically correct (in this case we add in the ‘contractible copula’ grammatical morpheme- the fancy word for is). I coach parents to expand their child’s utterance just by just one or two words. This makes the newly expanded phrase a perfect match for the child – it’s not too simple because it’s longer and more complex than what the child said, but it’s not so tough that it loses meaning for the child. 

Grow Your Child's Language

Back to the “Puppy outside” phrase. If we choose not to expand it…

We can extend this utterance instead by saying, “He’s barking.”  In this case, we’ve responded to the child’s utterance and we’ve stayed on the same topic (the puppy who is outside) but now we’ve added new information.  We’ve extended the conversation by adding a bit more information. This is the key to extension.

Expansion and extension seem to work best with toddlers and young preschoolers, or children whose language levels match those of a typical toddler or young preschooler. These children often imitate the newly expanded or extended utterances, which we think helps them to grow their language.  Plus, because we are responding to the child’s lead, we are tapping into whatever is interesting to the child at the moment, making our input (the language they hear) that much more salient, or pronounced, so that children are that much more likely to learn from it.

Research seems to indicate that many children learn language faster when their parents use more conversational language-learning strategies like expansion and extension, as compared to parents who are more directive with their children.  And use of these techniques is also linked to longer utterances in children – in other words, children who are exposed to these types of responsive language facilitation techniques seem to use longer sentences overall.  Seems like a good deal to me!

Other Resources
Everything You Need to Know Before Getting a Sleep Study Adelaide
Is a Home Sleep Study Brisbane Better Than In-Clinic Testing?

Communication Temptations

Communication Temptations: How Use Your Environment to Get Your Child Talking

Wondering how to get your child talking? We speech-language therapists have lots of tricks in our pockets to do just that. One of our very favorites involves enticing children to talk by creating what we call communication temptations (Wetherby and Prizant, 1989).This little strategy can be used to help a late-talker start talking, to help a toddler begin using two-word phrases, or to increase the chances that a young child with autism will begin communicating.

Communication temptations are pretty much just what they sound like: we set up the environment to tempt children to communicate with us. The rationale for using them is also a pretty simple one: a child is much more likely to communicate if he has a reason for doing so! 

Setting up communication temptations is easy and there are lots of ways to do so. Wetherby and Prizant (1989), who formalized the term, were pretty creative in their list of examples. They suggested things such as:

  • Offering your child something to eat you know he dislikes,
  • Putting a toy in an opaque bag and shaking it to get the child’s interest,
  • Putting your child’s hand in something sticky or gooey such as pudding, and
  • Waving bye-bye and saying “bye” as you put toys in a box three times, then pausing right before you put away the next toy.

Each of these ideas has one thing in common- the environment is set up so that a child is tempted to communicate about something (“no, I don’t want that!” “what is that?” “yuck” or “bye!”). Another form of communication temptation involves enticing a child to request. This is a great place to start for any child, but it’s especially good for kids with autism, because requesting is often the easiest form of communication for these children at first.

Communication Temptations

The steps to this type of communication temptation are as follows:

  1. Find an activity or an object that your child really enjoys.  Look for an activity that is easily stopped and started (e.g., bubbles or a swing) or an object that has multiple parts that you can hand to your child (e.g., crackers that he loves to eat, cars for a car track).
  2. Arrange the environment so that you create an obstacle to getting that object, but so that your child can see the object. For example, put your child’s favorite crackers up on a high shelf. Or, put the cars in see-through container he can’t open.
  3. Start the activity, have a bit of fun and then stop (put the lid on the bubbles or pull him up in the swing but don’t let him go) or give himoneitem (e.g., give him one cracker or one car). 
  4. Wait! Many parents forget this part, but it’s an important one. Give your child a chance to communicate first.  Ideally, we want him to communicate without us helping him (we want him to initiate the communication), so always wait first. See what he does. Look expectantly at him, like you are waiting for him to do something (which, of course, you are!)
  5. When he communicates with you (either verbally or nonverbally):
  • Give him what he wants and cheer him on–especially if it’s the first time he’s used that particular word or two-word phrase, or
  • Build on his communication just a bit to help him move into the next stage of speech and language development.

What you actually do for step number five depends completely on your child and his current level of communication. 

  • If your child isn’t yet using words, wait until he does something–anything– to indicate that he wants more (e.g., moves his body in anticipation, points, reaches); when he does (and he will!), say the word for what he wants, wait just a few moments more, and give it to him
  • If your child vocalizes to indicate he wants more but doesn’t actually say the word, say the word for him, wait just a few more seconds, and give him what he wants
  • If your child imitates the word, or even part of the word,  give him what he wants and cheer him on!
  • If your child always imitates your words, but doesn’t say them on his own, try waiting progressively longer before you say the word for what he wants; wait for one second and then say the word, then (the next time), wait for two seconds before saying the word, then (the next time, wait for three seconds before saying the word….and so on. If he gets frustrated, go back to waiting a shorter amount of time and build up again.
  • If your child uses one word to request more of the item, use expansion to put his word into a two-word phrase for him (your child: swing! you: “more swing!”), wait for just a few more moments, and then give him what he requested
  • If your child uses one word, you might also want to use a choice that involves two different two-word phrases (your child: cracker!; you: “big cracker or little cracker?”) and encourage him to use the two-word phrase to make a choice
  • If your child uses a longer phrase, but makes an error, you can correct his error by conversationally repeating what he said (your child: “wing!” you: “sssssswing!”) and encourage him to imitate you accurately.
  • You might also think about using communication temptations to teach your child to use baby signs or pictures to communicate. 

No matter what your child’s level, communication temptations are often a very successful way to create opportunities for your child to advance her communication skills. Tempt away!

Other Resources
Repetitive Books For Language Learning
Is a Home Sleep Study Brisbane Better Than In-Clinic Testing?

Kinds of Talk

All Kinds of Talk: Using Your Language to Change Your Child’s

It seems almost too simple to be true: To help your child learn to talk, you’ll need to….talk to your child. And yet as simple of a concept as it is, it’s also a very powerful one. So powerful, in fact, that it appears to have long-lasting effects on your child and his development.

One oft-cited research study, for example, found that the amount of “family talk” that surrounded a child was strongly related to that child’s vocabulary and their IQ at age three…and, importantly, still at age nine (Risley and Hart, 2006). This remained true even after variables such as socio-economic status were accounted for.  What’s more, the type of language families used with their child was also important.

Families in the study seemed to use two types of language; the “business” talk of telling children what needed to get done (do this, come here, put that down) and the more positive, engaging, conversational talk of describing the world to their children.  It was the families who used conversational talk with their children who talked more to their children….and the children in these families who had bigger vocabularies and higher IQ scores.

Kinds of Talk

When I am working as a pediatric-speech language pathologist, then, I almost always start by teaching families how to talk to their kids.  One of the first things I share with parents is how to use four specific types of “conversational” talking with their children: parallel talk, description, self-talk, and expansion.

  • Parallel talk occurs when a parent talks about what the child is doing (Eating soup. You’re eating soup!)
  • Description occurs when a parent describes an object to which the child is attending (Hot soup!)
  • Self-Talk occurs when a parent describes what the parent is doing as she does it. (Soup. Mama’s eating soup. Eat Soup), and
  • Expansion occurs when a parent takes what the child says and expands it by one or two words. (Child: Soup. Mom: Yummy soup!). 

Simple? Yes.  But research has shown that a child’s language can change for the better just by changing the language input they get from their parents. When parents are taught to use focused, simple language to describe what their child is doing and seeing, children make gains in their language skills (McLean and Cripe, 2000).  This isn’t to say parents should talk in short sentences all the time, of course. Children need to hear their parents talking in longer, conversational sentences as well.  It’s the balance between the short, focused language and the longer conversational sentences that seems to be the most effective.

Kinds of Talk

And, as it turns out, some parents may do this intuitively.  In 2005, Deb Roy, a cognitive scientist and director of MIT Media Lab’s Cognitive Machines Group, set his home up with cameras and microphones to record everything his son and his son’s caregivers said during the first two years of his son’s life.  Although he expected to find that the caregivers’ language got steadily more complex as his son aged, he actually found something very different.  When the caregivers talked to the baby, they didn’t necessarily use simple language and short sentences– at least not at first. But then–just as a new word was about to emerge in the toddler’s language–something changed.   The caregiver’s language became more and more simple….until the word emerged in the child’s language, and then the caregivers slowly made their language more complex again.  This pattern repeated itself across words and caregivers, even though the caregivers didn’t even know they were doing it. If this research stands up to time, it may show that parents who are really in tune with their babies and toddlers do a kind of dance with their child, where the child’s language influences the parents’ as much as the parents’ language influence the child’s.

It’s important to note that many children will also need additional strategies woven into their days as well: many parents talk a blue streak at their children only to find their children don’t talk back.  This is by no means the fault of the parents– some children just need more help then others getting started talking. This blog touches on many of the other strategies we use to help children learn to talk, and a good early intervention professional will help parents sort through these strategies and figure out how and when to apply them. The first step along the way, though, is almost always to teach parents to use those four types of conversation speech consistently and carefully and lovingly around their child.

All of this to get at one small, yet somehow very big, idea:  Talk to your baby, your toddler, your child. Talk about the things he sees, and the things he does, and the things that make him laugh.  And as you do, know that you are giving him one of the most powerful gifts of all: the gift of language.

Other Resources
Is a Home Sleep Study Brisbane Better Than In-Clinic Testing?
Everything You Need to Know Before Getting a Sleep Study Adelaide